Tag: cardiac arrest

  • Cardiac Arrest Sim 2016-04-06

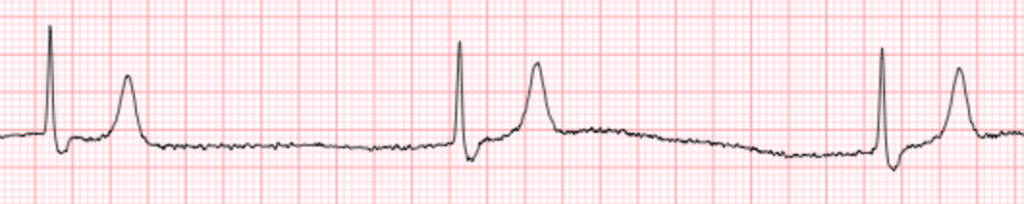
    ECG-hyperK

    A case of hyperkalaemia resulting in ventricular fibrillation followed by symptomatic bradycardia was simulated.

    The simulation highlighted some great learning points worth sharing:

    1. In cardiac arrest, it is worth having both medical and nursing team leaders, with physicians focusing on diagnosis and treatment of the underlying cause and nurses running the cardiac arrest algorithm.
    2. The use of role & name stickers helps clarify everyones part in the team and improve communication.
    3. Requests for additional medications  / CVC set up etc. should be directed to the nurse team leader clearly and slowly, ensuring the scribe has also heard.
    4. It is worth slowing down and communicating with full words rather than acronyms, and ensuring the mental model of current status (Update) and next steps (Priorities) is shared (Team Leaders should speak ‘UP‘!).
    5. Everyone in the team has a right and a responsibility to know what’s happening and to speak up if something seems wrong.

    The team did a great job, recognising and managing the VF and the symptomatic bradycardia, diagnosing the acute kidney injury with hyperkalaemia early and initiating appropriate therapy. Another manikin’s life saved!


    Here are some references related to the concepts discussed in the debrief:

    1. The variable ECG changes seen in hyperkalaemia (scroll down for the ECGs): http://lifeinthefastlane.com/ecg-library/basics/hyperkalaemia/

    2. Therapies for hyperkalaemia (scroll down to ‘Management of hyperkalaemia): http://lifeinthefastlane.com/hyperkalemia/
    – make sure you watch the ER video included in that post!

    3. In a Scandinavian resuscitation study, higher performing teams showed more effective information exchange and communication, and sharing mental models predicted effective medical management.
    Westli HK, Johnsen BH, Eid J, Rasten I, Brattebø G. Teamwork skills, shared mental models, and performance in simulated trauma teams: an independent group design. Scand J Trauma Resusc Emerg Med. 2010;18:47.
     

  • Cardiac Arrest Sim 2016-03-11

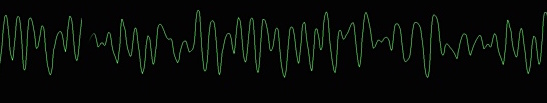
    vfisim

    A case of refractory ventricular fibrillation was simulated, outlining the challenges faced in a non-cardiac centre in a patient for whom standard Advanced Cardiac Life Support measures fail to achieve return of spontaneous circulation.

    The simulation highlighted some excellent approaches worth sharing:

    1. Having the nurse team leader ‘run the code’, ie. manage the cardiac arrest algorithm, was a highly effective way of allocating roles. This (a) ensured accurate timings, safe defibrillation, and effective task delegation (eg. drug preparation), and (b) freed the physician team leader’s cognitive capacity to focus on diagnosis, prognosis, effective management of the underlying cause, and steps ‘beyond the algorithm’.

    2. Including paramedics in the sim enabled the scenario to be run from the point prior to handover, enabling simulation of the Batphone call as well as the logistics of moving the patient from ambulance stretcher to bed.


    Here are some references related to the interventions tried and the concepts discussed in the debrief:

    Terminology: No flow / low flow vs ‘down time’ – http://resus.me/down-with-down-time/

    Meaney PA, Bobrow BJ, Mancini ME, Christenson J, de Caen AR, Bhanji F, et al.
    Cardiopulmonary Resuscitation Quality: Improving Cardiac Resuscitation Outcomes Both Inside and Outside the Hospital: A Consensus Statement From the American Heart Association. Circulation. 2013 Jul 22;128(4):417–35

    Art lines & titrated adrenaline: EMCrit Podcast 130 – Hemodynamic-Directed Dosing of Epinephrine for Cardiac Arrest

    Refractory VF: http://lifeinthefastlane.com/ccc/electrical-storm/ and http://www.emdocs.net/refractory-ventricular-tachycardia-approach-to-management/

    Esmolol: http://resus.me/esmolol-for-refractory-vf/