Communication skills in high acuity situations: Team, Patient, Consultation
The bat phone rings at 10 o’clock on a chilly Tuesday morning in your ED. You huddle for warmth around the radio with your resuscitation team…
The paramedics are bringing a 58 year old lady with an episode of syncope this morning and increasing shortness of breath over 2 days. She has a background of metastatic lung cancer.
Vital signs: RR 28, Sats 97% r/a, HR 112, BP 88/56, T 36.7, GCS 15.
The patient arrives and is alert, ‘chipper’ and able to give a comprehensive history. You request an ECG, VBG and CXR and perform a bedside echo, which demonstrates a large pericardial effusion with signs of cardiac tamponade.
You smoothly coordinate your team to stabilise the patient, ascertain her treatment goals and request specialist interventional cardiology consultation with the end goal of transferring her to the interventional suite for pericardial drainage.
She recovers well and is discharged home a few days later to meet her new Granddaughter born the following week.
We discussed the following learning points in debrief:
Optimise your team’s performance through effective use of the pre-arrival time
Brief your team as a whole involving medical and nursing team together
Use a structured communication tool for preparing your team for a resuscitation for example the “Team Briefing Model”, see link below
Consider asking all team members to verbalise their roles and priorities to one another prior to the patients’ arrival
Use the opportunity to reinforce mutual respect amongst team members to encourage speaking up and making suggestions
Even though it’s a resuscitation, allow the patient opportunity to set their own agenda
It is natural to want to use closed questions in a high acuity situation to establish facts, highlight red flags and rapidly rule in and out potential differentials. Evidence shows that open questions gather more information, more quickly than closed questions. And you will very quickly establish your patient’s main concerns, ideas and expectations
When consulting specialists over the phone use a structured approach, be polite and collaberative and most of all, be honest!
Use a telephone consult structuring tool such as CONSULT or 5 Cs (see below)
At night, allow at least a minute for the phone call recipient to wake up. Fill this time by politely introducing yourself (name, role, level of experience, location), checking who you are speaking to and giving details of the patient you are calling to discuss
Quickly move on to the key question, which should be specific, focused and brief. Examples: “I need you to come in urgently to assist with xyz”; “I need your advice on whether to intubate the patient with hypercapnic respiratory failure and advanced, end stage COPD”; “I need you to come in to drain a pericardial effusion causing cardiac tamponade”
Don’t panic if you can’t answer some of the more technical questions the specialist may ask. Be honest, don’t lie. Re-iterate your level of experience and your primary question
“A 24 year old Man was brought into ED by ambulance after being found unresponsive at home by his Girlfriend.
He had been out with mates the night before and returned in the early morning intoxicated with alcohol and cocaine.
He appeared ‘slate blue’ in colour with RR 40, sats 85% 15L NRBM, HR 110, BP 150/90, GCS 8, T 37.1, BSL 18.”
VBG
pH 7.07
pCO2 58
pO2 20
HCO3 16
BE -12.4
K+ 6.3
Chloride 114
Glucose 19
Lac >20
OxyHb 12.0%
Deoxyc Hb 0.0%
CarboxyHb 4.2%
MetHb 63.9%
“He was diagnosed with methaemaglobinaemia secondary to likely benzocaine ingestion (used as a cutting agent in cocaine). He was treated with methylene blue and intubated for low GCS, then transferred to ICU where he was extubated successfully the next day.”
Key Learning Points
Technical:
Diagnosis
Methaemoglobinaemia occurs when ferrous ions (Fe2+) of haem are oxidized to the ferrous state (Fe3+) and then cannot bind to O2
People may present with knowledge of a congenital methaemaglobinaemia but most acute cases are caused by ingestion of a toxin:
aniline dyes
benzene derivatives
chloroquine
dapsone
prilocaine
metoclopramide
nitrites (nitroglycerin, NO, sodium nitroprusside, sodium nitrate)
sulphonamides
Suspect if patient presents with suspicion of toxic ingestion plus altered mental status, blue/grey cyanotic skin, poor O2 sats unresponsive to O2 administration (classically 85%) and brown/’chocolate’ coloured blood
Treatment
Treat with usual supportive treatment/ resuscitation and follow usual ACLS protocol
Give methylene blue 1-2mg/kg IV stat – this can now be found in the resus drug cupboard
It comes in 50mg/5ml ampoules and should be given neat at 0.1-0.2ml/kg and then repeated once at 30-60mins if MetHb levels are not falling
Call poisons for advice early on 13 11 26
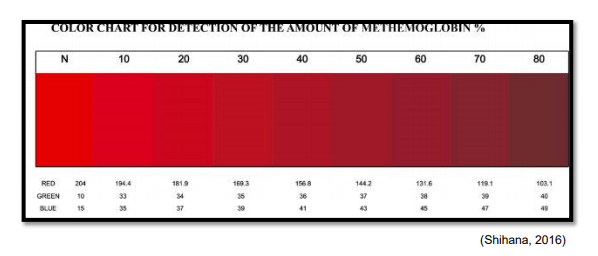
Remember when MetHb concentrations are ‘massive’ you may get an ‘error’ reading on your VBG result. In this case, use the colour chart for the estimation of the MetHb concentration in blood
Non-Technical
Utilise available resources
Protocols for the administration of IV drugs can be found on the L drive: Emergency -> Public -> Clinical Policies and Procedures -> Pharmacology -> Emergency and Intensive Care drug Protocols
Call poisons early on 13 11 26
Communication
Telephone calls to poisons or other specialists: Make sure you know what you are asking for. Is it for hands-on assistance? Or for specific management advice. The team leader should brief you prior to making the call but if you are ensure, feel empowered to ask.
Regular summaries enable the team as a whole to take stock of the current situation and allows the team leader to share his/her clinical reasoning and priorities with the team. It also allows for questions or concerns to be raised by team members.
Ensure all key information is fed back to the team leader and all key decisions are communicated via the team leader. This is especially important when there is more than one senior clinician in the team who may be making decisions. Remember the team leader is the only team member with complete cognitive oversight of the situation.
This hypothetical case was simulated today with resident medical staff and nursing staff.
The Case
An obese 40 year male with type 2 diabetes mellitus presented in status epilepticus.
He had taken an oral hypoglycaemic agent but rather than have breakfast he went on a pub crawl to celebrate his 40th birthday. He then collapsed and had tonic clonic seizures. He had been given intramuscular midazolam by paramedics.
The Objectives
Prepare for patient arrival, organise team and allocate roles. Manage airway, control seizures, identify and treat the underlying cause.
The Learning Points – Clinical
1. Position is EVERYTHING in airway management. Don’t forget to align the external auditory meatus with the suprasternal notch horizontally (this applies to all ages and sizes of patient), with the face parallel to the ceiling.
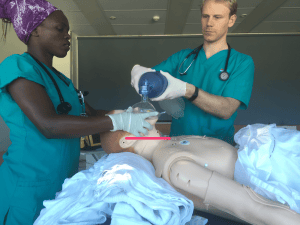
2. Optimal bag mask ventilation involves a two person technique, allowing maintenance of an effective jaw thrust and good mask seal, with the use of airway adjuncts (oro- or naso-pharyngeal airways, or both):
3. Although the intraosseous route is preferred if there are delays in securing vascular access, it is not ideal for sampling for laboratory investigations. Blood can be taken from a large venous or arterial stab (eg. femoral vein) simultaneous to intraosseous insertion.
4. Intraosseous access does not have to be limited to the tibia! In some patients, the humeral head site may be preferable.
5. Not every comatose patient needs to be intubated. Plot the trajectory of their clinical state: if they’re improving and you’ve fixed the underlying cause, they may wake up (eg. post-hypoglycaemia or post-ictal). Actively support the airway in the meantime and if you need to set up for intubation use the checklist as a guide.
The Learning Points – Non-Clinical
1. Having a nursing and medical team leader working side by side works well in resuscitation due to the multiple tasks needing to be allocated to staff who are at various points on the skill-mix spectrum.
2. Medication orders should be written down to minimise misunderstanding and drug errors. It is the medical team leader’s responsibility to make this happen.
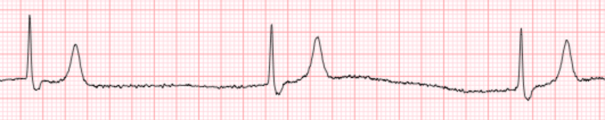
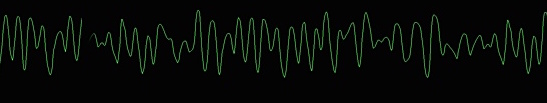
A case of hyperkalaemia resulting in ventricular fibrillation followed by symptomatic bradycardia was simulated.
The simulation highlighted some great learning points worth sharing:
In cardiac arrest, it is worth having both medical and nursing team leaders, with physicians focusing on diagnosis and treatment of the underlying cause and nurses running the cardiac arrest algorithm.
The use of role & name stickers helps clarify everyones part in the team and improve communication.
Requests for additional medications / CVC set up etc. should be directed to the nurse team leader clearly and slowly, ensuring the scribe has also heard.
It is worth slowing down and communicating with full words rather than acronyms, and ensuring the mental model of current status (Update) and next steps (Priorities) is shared (Team Leaders should speak ‘UP‘!).
Everyone in the team has a right and a responsibility to know what’s happening and to speak up if something seems wrong.
The team did a great job, recognising and managing the VF and the symptomatic bradycardia, diagnosing the acute kidney injury with hyperkalaemia early and initiating appropriate therapy. Another manikin’s life saved!
Here are some references related to the concepts discussed in the debrief:
2. Therapies for hyperkalaemia (scroll down to ‘Management of hyperkalaemia): http://lifeinthefastlane.com/hyperkalemia/
– make sure you watch the ER video included in that post!
3. In a Scandinavian resuscitation study, higher performing teams showed more effective information exchange and communication, and sharing mental models predicted effective medical management.
Westli HK, Johnsen BH, Eid J, Rasten I, Brattebø G. Teamwork skills, shared mental models, and performance in simulated trauma teams: an independent group design. Scand J Trauma Resusc Emerg Med. 2010;18:47.
A case of refractory ventricular fibrillation was simulated, outlining the challenges faced in a non-cardiac centre in a patient for whom standard Advanced Cardiac Life Support measures fail to achieve return of spontaneous circulation.
The simulation highlighted some excellent approaches worth sharing:
1. Having the nurse team leader ‘run the code’, ie. manage the cardiac arrest algorithm, was a highly effective way of allocating roles. This (a) ensured accurate timings, safe defibrillation, and effective task delegation (eg. drug preparation), and (b) freed the physician team leader’s cognitive capacity to focus on diagnosis, prognosis, effective management of the underlying cause, and steps ‘beyond the algorithm’.
2. Including paramedics in the sim enabled the scenario to be run from the point prior to handover, enabling simulation of the Batphone call as well as the logistics of moving the patient from ambulance stretcher to bed.
Here are some references related to the interventions tried and the concepts discussed in the debrief:
Meaney PA, Bobrow BJ, Mancini ME, Christenson J, de Caen AR, Bhanji F, et al.
Cardiopulmonary Resuscitation Quality: Improving Cardiac Resuscitation Outcomes Both Inside and Outside the Hospital: A Consensus Statement From the American Heart Association. Circulation. 2013 Jul 22;128(4):417–35